Caleb Williams Injury Update: QB Seen Walking Post-Game
Caleb Williams Post-Game Injury Update: Quarterback Seen Walking Without Crutches
1. Breaking Update: Caleb Williams Locker Room Status
Eyewitness Reports: Walking Without Crutches
Reporters entering the post-game locker room observed quarterback Caleb Williams moving under his own power. Williams did not require crutches, a walking boot, or physical support from team trainers. Media members present noted a slight limp in his gait as he moved between his locker stall, the training room, and the post-game interview area.
Weight-bearing mobility immediately following a game serves as an essential initial diagnostic benchmark. The ability of an athlete to bear full body weight without assistive devices reduces the probability of immediate high-grade skeletal disruptions, complete tendon ruptures, or major joint instability. While a slight limp indicates localized pain, muscular guarding, and early inflammatory response, unassisted ambulation confirms basic functional integrity across the lower-leg kinetic chain.
The visual evidence of a mild limp points toward acute lower-extremity trauma, such as an ankle sprain, foot contusion, or mild knee strain. Muscle guarding occurs naturally after high-impact contact as surrounding muscle groups contract involuntarily to stabilize an injured joint. Williams navigating post-game procedures without immobilization equipment provides an initial positive sign regarding baseline stability.
Post-Game Medical Steps and Immediate Assessments
Sideline medical personnel performed initial physical assessments immediately following the play. These tests included manual stability checks, joint line palpation, and range-of-motion assessments.
Following the final whistle, the training staff initiated locker room stabilization protocols. Key interventions applied at this stage include:
- Cryotherapy and Compression: Rapid application of targeted ice wraps and pneumatic compression sleeves to mitigate edema.
- Anti-Inflammatory Management: Early administration of non-steroidal anti-inflammatory drugs (NSAIDs) to regulate acute pain and swelling.
- Physical Palpation: Re-examination of ligamentous endpoints after the athlete cooled down from active exertion.
The medical team scheduled standard follow-up diagnostic imaging for the morning after the game. Baseline digital X-rays assess structural integrity and rule out micro-fractures, avulsions, or acute bone trauma. Magnetic Resonance Imaging (MRI) scans evaluate soft-tissue integrity, targeting the anterior talofibular ligament, calcaneofibular ligament, syndesmotic structures, deltoid complexes, or knee collateral ligaments.
2. In-Game Breakdown: The Injury Sequence
Key Play Analysis
The injury occurred during a contested offensive series when Williams faced pressure within the pocket. As the pocket collapsed, Williams attempted an off-platform maneuver to avoid an interior pass rusher.
During the release phase of the pass, a defensive lineman made contact with Williams’ lower extremities. The defender’s momentum carried through the lower leg, forcing a torsional or lateral load onto the planted foot. The contact caused an unnatural pivot, applying stress to the joint capsule before Williams fell to the turf.
Biomechanical breakdown reveals two key stress points:
- Eversion or Inversion Force: The angle of the defender’s landing forced either an inward or outward roll on the ankle joint.
- Axial Loading: The downward weight of the defender compromised normal knee and ankle flexion, compressing the joint surfaces during active internal rotation.
Williams remained on the ground briefly, signaling discomfort in his lower leg before receiving attention from medical staff.
+-------------------------------------------------------------------+
|                     INJURY SEQUENCE SUMMARY                       |
+---------------------+---------------------------------------------+
| Phase               | Description                                 |
+---------------------+---------------------------------------------+
| Pocket Collapse     | Defensive pressure forces off-platform step |
| Contact Point       | Rusher lands across lower leg/foot          |
| Joint Mechanism     | Torsional rotation under axial load         |
| Primary Symptom     | Immediate discomfort, localized tenderness  |
| Post-Snap Reaction  | Brief stay on turf, unassisted exit to bench|
+---------------------+---------------------------------------------+
Sideline Reaction and Protocol
Upon reaching the sideline, Williams was directed to the blue medical tent for private evaluation. Athletic trainers removed his footwear and tape on the affected side to inspect the area for rapid swelling, deformities, or focal hematomas.
The medical staff performed standard stress tests:
- Anterior Drawer Test: Assessing anterior talofibular ligament laxity.
- Talar Tilt Test: Checking calcaneofibular integrity.
- Squeeze Test: Evaluating potential high-ankle syndesmotic separation.
Trainers applied fresh spat-taping to reinforce the joint capsule and provide external stability. Williams tested the leg with dynamic drop-backs, lateral shuffles, and short sprint starts along the sideline. Based on pain tolerance, clinical stability, and game context, the coaching staff and medical team evaluated whether to re-insert Williams or preserve the starting quarterback to prevent compounding tissue damage.
3. Medical Outlook: Evaluating Lower-Body Trauma
Implications of Mobility Without Assistive Devices
The absence of crutches directly impacts the differential diagnosis. In professional sports medicine, assistive devices are mandatory if clinical evaluations indicate structural failure, gross instability, or risk of displacement.
+------------------------------------------------------------------------+
|               CLINICAL SIGNIFICANCE: UNASSISTED WALKING                |
+----------------------------+-------------------------------------------+
| Condition Category         | Clinical Implication                      |
+----------------------------+-------------------------------------------+
| High-Grade Tendon Tear     | Highly Unlikely (requires immobilization)  |
| Displaced Bone Fracture    | Highly Unlikely (non-weight bearing)      |
| Grade 1 Soft-Tissue Sprain | High Probability (microscopic fiber tears)|
| Grade 2 Moderate Sprain    | Moderate Probability (partial tear/limp)  |
| Deep Bone Bruise/Contusion | Moderate Probability (focal pain on step) |
+----------------------------+-------------------------------------------+
Unassisted walking demonstrates that the primary weight-bearing bones (tibia, fibula, talus, calcaneus) and primary stabilizing tendons (Achilles, patellar) maintain sufficient mechanical integrity to transmit body loads. It rules out complete structural disruptions that mandate immediate non-weight-bearing protocols.
Typical Recovery Timelines for Lower-Leg Sprains
Lower-extremity trauma in NFL quarterbacks typically falls into three main structural categories: standard lateral ankle sprains, syndesmotic (high) ankle sprains, or collateral knee sprains (MCL).
+----------------------------------------------------------------------+
|                     TYPICAL RECOVERY TIMELINES                       |
+---------------------------+---------------+--------------------------+
| Injury Type               | Grade / Level | Expected Timeline        |
+---------------------------+---------------+--------------------------+
| Lateral Ankle Sprain      | Grade 1       | 1 to 7 days              |
| Lateral Ankle Sprain      | Grade 2       | 1 to 3 weeks             |
| High Ankle (Syndesmotic)  | Grade 1       | 1 to 2 weeks             |
| High Ankle (Syndesmotic)  | Grade 2       | 3 to 6 weeks             |
| Knee MCL Sprain           | Grade 1       | 1 to 2 weeks             |
| Foot/Ankle Contusion      | Mild/Moderate | 3 to 7 days              |
+---------------------------+---------------+--------------------------+
The initial 48 hours dictate the trajectory of recovery. Inflammation peaks within 24 to 48 hours post-trauma. The objective of the medical team during this phase centers on the RICE/POLICE framework:
- Protection: Bracing or rigid taping during movement.
- Optimal Loading: Gentle active range-of-motion drills to stimulate lymphatic drainage without aggravating torn fibers.
- Ice/Cryotherapy: Modulating nerve conduction velocity to reduce acute pain perception.
- Compression: Continuous mechanical pressure to prevent excess extracellular fluid accumulation.
- Elevation: Reducing hydrostatic pressure in the distal limb.
4. Strategic and Tactical Implications for the Offense
Impact on Williams’ Play Style
Williams’ offensive profile relies on multi-platform throwing ability, sudden pocket evasion, and off-schedule playmaking. Lower-extremity injuries degrade an athlete’s physical output across several distinct performance areas:
                  +-----------------------------------+
                  |   LOWER-BODY TRAUMA IN THE QB     |
                  +-----------------+-----------------+
                                    |
            +-----------------------+-----------------------+
            |                                               |
            v                                               v
+-----------------------+                       +-----------------------+
|  KINETIC CHAIN LOSS   |                       | TACTICAL COMPROMISE   |
+-----------------------+                       +-----------------------+
| * Reduced torque gen. |                       | * Decreased scrambles |
| * Off-platform limits |                       | * Strict pocket focus |
| * Slower plant-to-cut |                       | * Quick release focus |
+-----------------------+                       +-----------------------+
1. Kinetic Chain Efficiency and Throwing Velocity
Passing power originates from ground reaction forces generated through the lower limbs. The back foot anchors rotational torque, while the front leg converts linear momentum into rotational arm speed. An unstable or painful lower extremity prevents full weight transfer, forcing the quarterback to rely primarily on upper-body and core mechanics. This decreases pass velocity on intermediate and deep boundary throws.
2. Off-Platform Escapes and Scrambling
Williams relies on explosive lateral cutting to escape interior pressure. A compromised lower limb limits lateral deceleration and acceleration. Defenses can deploy disciplined pass rushes without the continuous threat of the quarterback breaking contain to extend plays.
3. Pocket Adaptations
The offensive coordinator must adjust the scheme if Williams plays through limited mobility:
- Shotgun and Pistol Alignments: Minimizing traditional 5-step and 7-step under-center drops that demand rapid backward transitions.
- Quick-Game Passing (1-to-3 Step Concepts): Designing high-percentage, short-yardage throws (slants, bubble screens, shallow drags) that release the ball under 2.5 seconds.
- Max Protection Packages: Utilizing tight ends and running backs in pass-blocking sets to keep the pocket clean and prevent direct contact.
Backup Quarterback Preparation and Practice Reps
When the starting quarterback sustains an injury, the coaching staff restructures weekly preparation.
During a standard NFL game week, the starting quarterback takes roughly 80% to 90% of active first-team repetitions during practice installations on Wednesday and Thursday. If Williams is limited, the primary backup quarterback absorbs those primary reps.
+--------------------------------------------------------------------+
|                  PRACTICE REP DISTRIBUTION SPLIT                   |
+------------------------+-------------------+-----------------------+
| Quarterback Status     | Starter Rep Share | Backup Rep Share      |
+------------------------+-------------------+-----------------------+
| Standard Week          | 85% - 90%         | 10% - 15%             |
| Starter Limited (Ques) | 40% - 50%         | 50% - 60%             |
| Starter Sidelined (Out)| 0% (Mental Reps)  | 100%                  |
+------------------------+-------------------+-----------------------+
The backup quarterback must establish timing with starting wide receivers, execute game-plan checks against specific defensive fronts, and develop rhythm with the starting center during cadence variations. The coaching staff prepares dual game plans: one utilizing Williams’ mobility and improvisation, and an alternative tailored to the backup’s pocket-passing skill set.
5. Week-Ahead Outlook and Availability Projection
Official Practice Injury Report Benchmarks
The NFL requires teams to release practice participation reports on Wednesday, Thursday, and Friday leading up to a weekend game. Williams’ status will be cataloged under standard league designations:
+------------------------------------------------------------------------+
|                     PRACTICE PARTICIPATION TIERS                       |
+-------------------------------+----------------------------------------+
| Designation                   | Definition                             |
+-------------------------------+----------------------------------------+
| Did Not Participate (DNP)     | Zero participation in team or dynamic  |
|                               | individual football drills.            |
| Limited Participation (LP)    | Took part in select periods or drills; |
|                               | rep volume managed below full load.    |
| Full Participation (FP)       | Completed all standard team reps       |
|                               | without physical restrictions.         |
+-------------------------------+----------------------------------------+
The progression across these three days indicates game-day readiness:
- Wednesday: High probability of a Did Not Participate (DNP) or Limited Participation (LP) designation to allow acute inflammation to subside while Williams receives treatment.
- Thursday: The crucial evaluation day. A transition from DNP to Limited indicates positive tissue recovery and the ability to test the joint in team drills.
- Friday: Final practice designation. A status of Limited or Full confirms the baseline needed for an active game-day designation.
+------------------------------------------------------------------------+
|                      FRIDAY GAME STATUS CRITERIA                       |
+---------------------+--------------------------------------------------+
| Game Status         | Historical Availability Probability              |
+---------------------+--------------------------------------------------+
| Questionable        | 50% chance of playing in the upcoming game       |
| Doubtful            | Unlikely to play (less than 25% chance)          |
| Out                 | Not cleared for game participation               |
+---------------------+--------------------------------------------------+
Next Matchup Dynamics
The upcoming opponent dictates the organizational tolerance for risk. Facing an aggressive defensive front with high blitz rates and elite edge rushers elevates the risk of re-injury.
Key strategic factors evaluated by the staff include:
- Pass Rush Profile: Facing high-pressure defenses demands maximum mobility for self-preservation. A compromised quarterback risks taking additional sacks and heavier hits.
- Field Surface: Playing on synthetic turf versus natural grass influences joint stress. Artificial turf generates higher traction forces and greater impact stress on ankles and knees.
- Division and Playoff Standings: The long-term health of a franchise quarterback takes precedence over a single regular-season contest unless high-stakes playoff positioning directly demands playing through manageable discomfort.
Frequently Asked Questions (FAQ)
Was Caleb Williams seen using crutches after the game?
No. Caleb Williams walked out of the stadium and moved through the locker room under his own power without crutches or an immobilizing boot. Media members present observed a slight limp.
What is the specific nature of Caleb Williams’ injury?
The exact diagnosis is confirmed via follow-up diagnostic imaging (X-rays and MRI). Initial observations indicate a mild-to-moderate lower-extremity sprain or contusion sustained from direct contact in the pocket.
Did Caleb Williams return to the game after sustaining the limp?
Williams was evaluated on the sideline in the medical tent. Return-to-play decisions during the contest depended on joint functional stability, pain management, and game-state strategy.
Will Caleb Williams miss upcoming practice sessions?
Early-week practices—especially Wednesday walkthroughs—routinely feature modified or limited reps for starting quarterbacks dealing with lower-body trauma to manage swelling and accelerate recovery.
Who takes first-team reps if Caleb Williams is sidelined?
The primary backup quarterback on the active depth chart takes over first-team repetitions during practice installations to prepare for the upcoming matchup.
Artikel Terkait
-
 Barcelos 'Stable, Alert' After UFC Main Event TKO Loss
-
 CFP Picture: Week 4 Standings & 12-Team Bracket Predictions
-
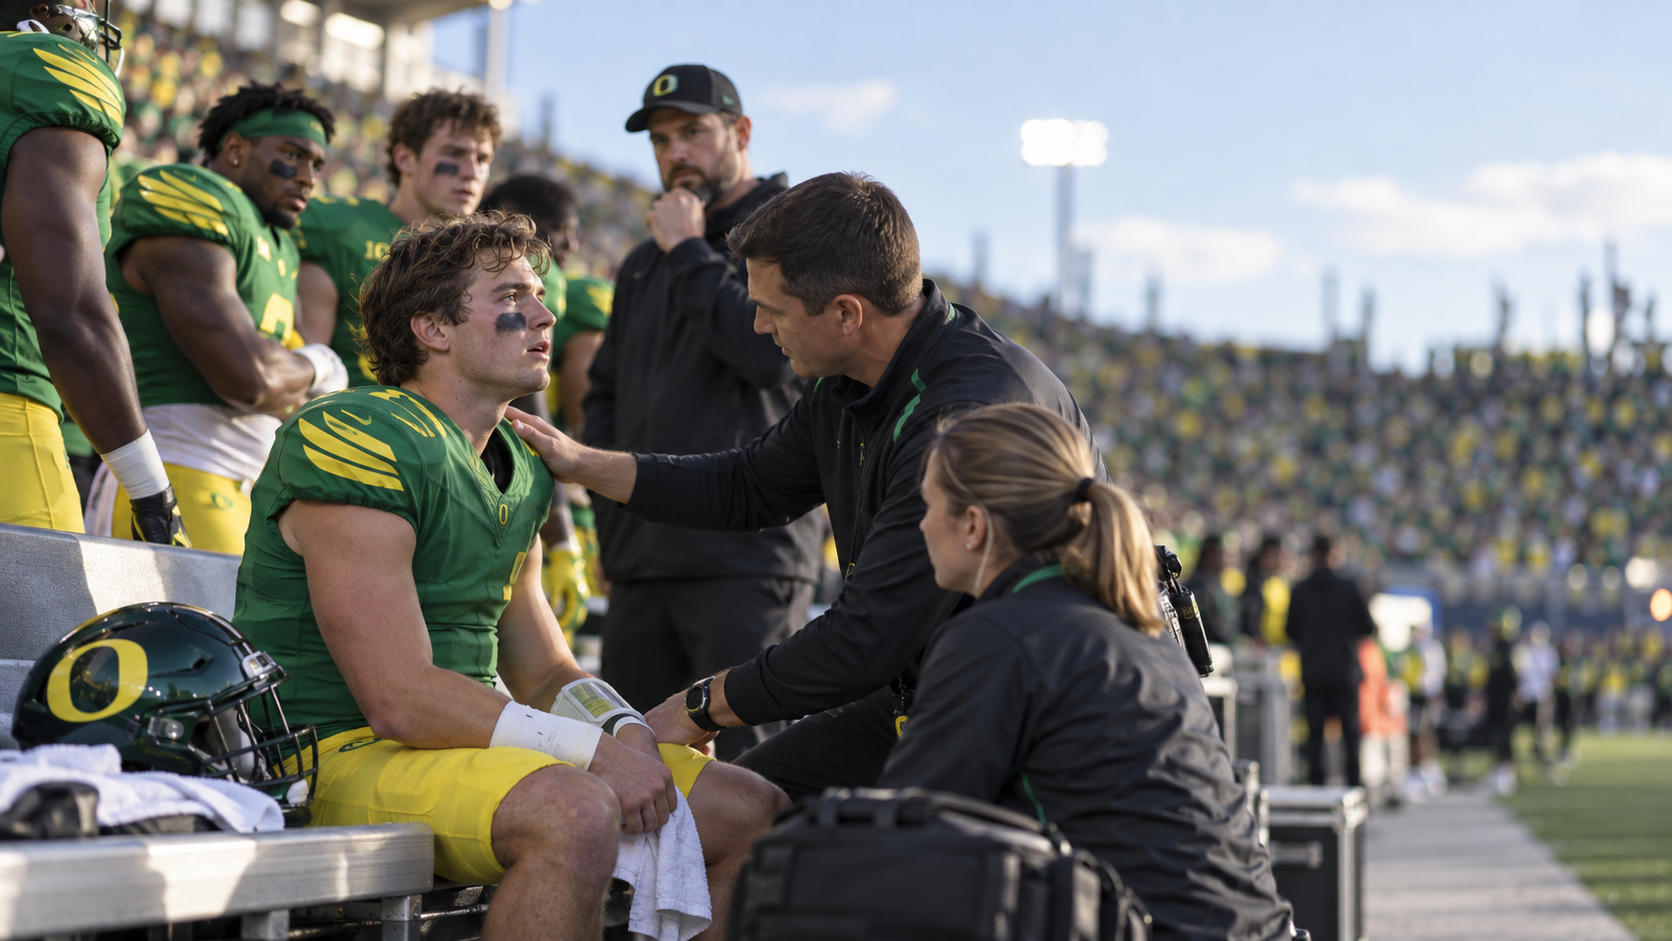 Dante Moore Injury Update: Oregon QB Outlook & Recovery
-
 What Nebraska Football Proved Against Michigan State
-
 Presidents Cup: How to Watch Saturday Action
-
 Manchester City Charges: Premier League Era Tainted